


-
- Global AMC MENU
- NEWS
- RESEARCH
- PEOPLE
- Introduction


Professor Jae Kwang Yun’s Team at Asan Medical Center Analyzes 25,000 Patients Who Underwent Surgery for Non-Small Cell Lung Cancer in Korea and the United States
Five Year Survival Rates Decline Significantly with Increasing Numbers of Metastatic Lymph Nodes: 68.7% for One Node vs. 44.4% for Five or More
“Combining the Number of Metastatic Lymph Nodes with the Existing Staging System Can Improve Risk Prediction and Support Personalized Treatment”
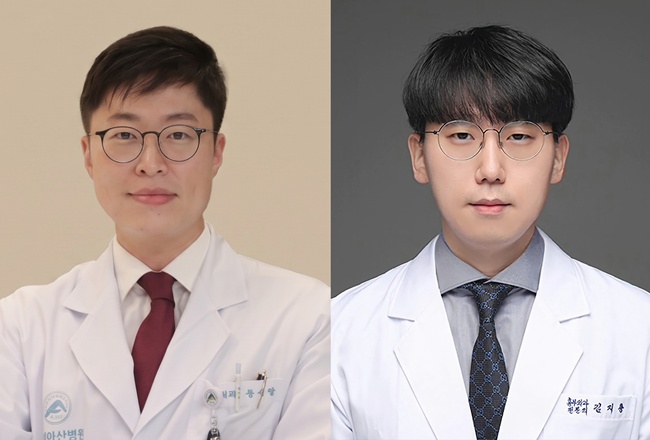
▲ (From left) Professors Jae Kwang Yun and Ji Yong Kim from the Department of Thoracic and Cardiovascular Surgery at Asan Medical Center
Recent research has found that, when predicting outcomes for patients with non-small cell lung cancer (NSCLC) who undergo surgery, the number of metastatic lymph nodes, in addition to their location, is an important indicator of survival.
A research team led by Professors Jae Kwang Yun and Ji Yong Kim from the Department of Thoracic and Cardiovascular Surgery at Asan Medical Center analyzed a large cohort of 25,000 patients with NSCLC who underwent surgery in South Korea and the United States. The team identified differences in survival rates according to the number of metastatic lymph nodes and established prognostic criteria based on these findings.
The TNM staging system, which evaluates tumor size (T), the location of lymph node etastasis (N), and distant metastasis to other organs (M), is currently the standard method for determining the stage of lung cancer. However, patients with the same pattern of lymph node metastasis can have different prognoses, highlighting the need for additional assessment criteria to more accurately predict survival rates and patient risk.
The research team first analyzed 18,294 patients who underwent lung cancer surgery and were registered in the U.S. National Cancer Institute’s Surveillance, Epidemiology, and End Results (SEER) database to establish new prognostic criteria based on the number of metastatic lymph nodes. To further strengthen the objectivity and reliability of these criteria, the team then conducted an independent validation using data from 7,386 patients with NSCLC who underwent surgery at Asan Medical Center.
The analysis revealed clear differences in survival rates when patients were divided into four groups according to the number of metastatic lymph nodes: zero, one, two to four, and five or more. The five year survival rates among patients treated at Asan Medical Center were 85.6% for those with no lymph node metastasis, 68.7% for those with one metastatic lymph node, 61.2% for those with two to four, and 44.4% for those with five or more. These findings confirmed that survival rates declined progressively as the number of metastatic lymph nodes increased.
Notably, among patients with only one metastatic lymph node, survival rates did not differ significantly according to the existing lymph node stage. In contrast, patients with five or more metastatic lymph nodes had poorer prognoses even within relatively advanced stages.
The research team conducted multiple statistical analyses to validate the predictive accuracy of the classification system based on the number of metastatic lymph nodes. The results showed no statistically significant differences between the new classification system and the 9th edition TNM N classification in key measures, including the concordance index (C-index) for predicting overall survival and the area under the curve (AUC), which measures predictive accuracy over time.
The new classification system also demonstrated comparable performance in the net reclassification improvement (NRI), an index used to assess differences in predictive performance between two models. These findings provided scientific evidence that the new classification system offers prognostic prediction capabilities comparable to those of the existing global standard.
The findings were recently published in the International Journal of Surgery (impact factor: 10.1), a leading journal in the field of surgery.
Professor Jae Kwang Yun of the Department of Thoracic and Cardiovascular Surgery at Asan Medical Center said, “The significance of this study lies in demonstrating through data from a large cohort that the number of metastatic lymph nodes, as well as their location, provides important prognostic information when evaluating lymph node metastasis in lung cancer.”
He added, “Combining the new classification system based on the number of metastatic lymph nodes with the currently used 9th edition TNM staging system could enable more precise assessment of patients’ risk and greatly help establish personalized treatment and patient monitoring plans.”
ASAN MEDICAL CENTER
BROCHURE DOWNLOAD
Sharing your hope
ASAN MEDICAL CENTER
